It’s not an ache. It’s a demon from hell.
By Alfredo Parra-Hinojosa
October 12, 2026
Cross-posted on the EA Forum.
Impressions from the 21st Annual U.S. Cluster Headache Patient Conference, organized by Clusterbusters.
On the morning of the last day of the conference, E. was hanging out with other “clusterheads” outside the conference hotel when he started having a cluster headache attack. Before he could go back to his hotel room, J. offered E. his DMT vape pen. J. is chronic—he gets attacks every day—so he never goes anywhere without his vape pen. He has successfully aborted hundreds of attacks with DMT in the two years he’s been using it. Many years ago, E. had done DMT recreationally, but he had never used it to abort an attack, despite having had cluster headaches for decades.
“Do a 2-second pull, and hold it in as long as you can,” said J. to E. A few seconds later, E. could feel some effects, but the pain was still there. So he took another 2-second pull. He then stared intently at a tree in front of him for about 30 seconds. Then, his face transformed. He smiled, in utter disbelief. He started laughing and crying. The pain was completely gone. He felt clear-headed. He had never felt the pain fizzle away so quickly. The other patients who were there and were familiar with that feeling, offered him a hug. “We know,” they said. “We know.”
It was not uncommon for attendees to get attacks during the conference in Chicago. There were about 150 patients, many of them chronic or in cycle. As such, there was a room full of oxygen tanks for participants to use freely (high-flow oxygen is the standard, recommended treatment to abort attacks).

Clusterbusters, the leading cluster headache advocacy and research organization, has been organizing this annual patient conference for 21 years. This year, they invited me as a representative of ClusterFree, and especially encouraged me to spread the word about our latest project, ClusterInfo.
It’s common to hear patients describe their first Clusterbusters conference as “life-changing” and even a “life-saver.” Many of them spend years suffering alone, being told by well-meaning friends and family members things like “oh, I also get headaches! Have you tried Excedrin?” It takes many patients a few years to even learn the term “cluster headache.” So, suddenly being in a room full of people who really understand the torture they endure is, to say the least, cathartic.
This was most obvious during the first session of the first day. It’s a tradition to let all first-timers briefly introduce themselves to the rest of the room. The organizers passed around boxes of tissues, knowing there would be tears. And tears were shed indeed—for example, by a man in his forties, desperate to learn more about treatments that could help his teenage daughter, who couldn’t attend herself because she was in poor health.
For me, the conference was special in a different way. I’ve been working on cluster headaches nearly full time for about two years. Before that, I had never met anyone with cluster headaches. In these two years, I’ve met only a handful of patients one-on-one, though I chat with many more online almost daily, for example on the ClusterBuds Discord server (of which I’m also a moderator), on Reddit, and on various Facebook support groups. I think about cluster headaches every day, so being in a room full of the people behind the numbers was a bit surreal.
This was also the first time the conference included a pediatric track, so a few kids attended. While cluster headaches most commonly start in adulthood, a Clusterbusters survey found that about 28% of respondents started getting their headaches before the age of 18. The organizers emphasized the urgent need for more focus on children, sharing the story of an 11-year-old girl with cluster headaches who tried to take her life the day before the conference began.
The second day of the conference featured two plenary sessions on DMT. The first one was a talk by Dr. Erik Zorrilla, who works with Dr. Emmanuelle Schindler at Yale. Dr. Schindler’s team is the only team in the US studying psychedelics for headache conditions. Dr. Zorrilla shared more detailed results from their survey of 88 patients who used DMT to abort their attacks. Some highlights include:
- 87% reported a complete (100%) or near complete (99%) reduction in pain (70% and 17% of respondents, respectively)
- 3% reported a 75% reduction in pain, 5% a 50% reduction, 2% a 25% reduction, and only 2% reported it being not effective
- 76% reported it working in under 1 minute (and 96% in under 5 minutes)
- 83% reported it working every time without fail (48%) or almost every time (35%)
- 87% reported it not losing efficacy over time (no tolerance)
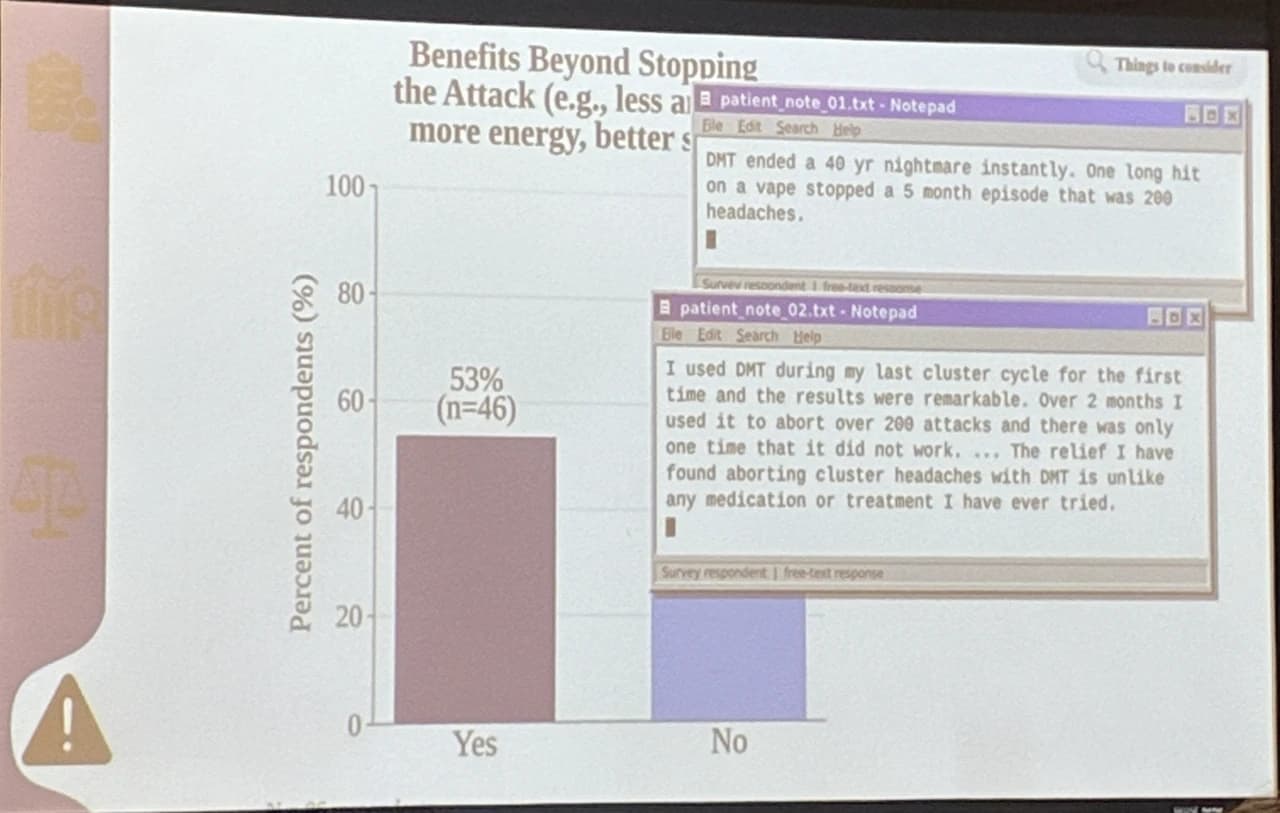
- 53% reported getting other benefits from DMT, such as less anxiety, more energy, or better sleep
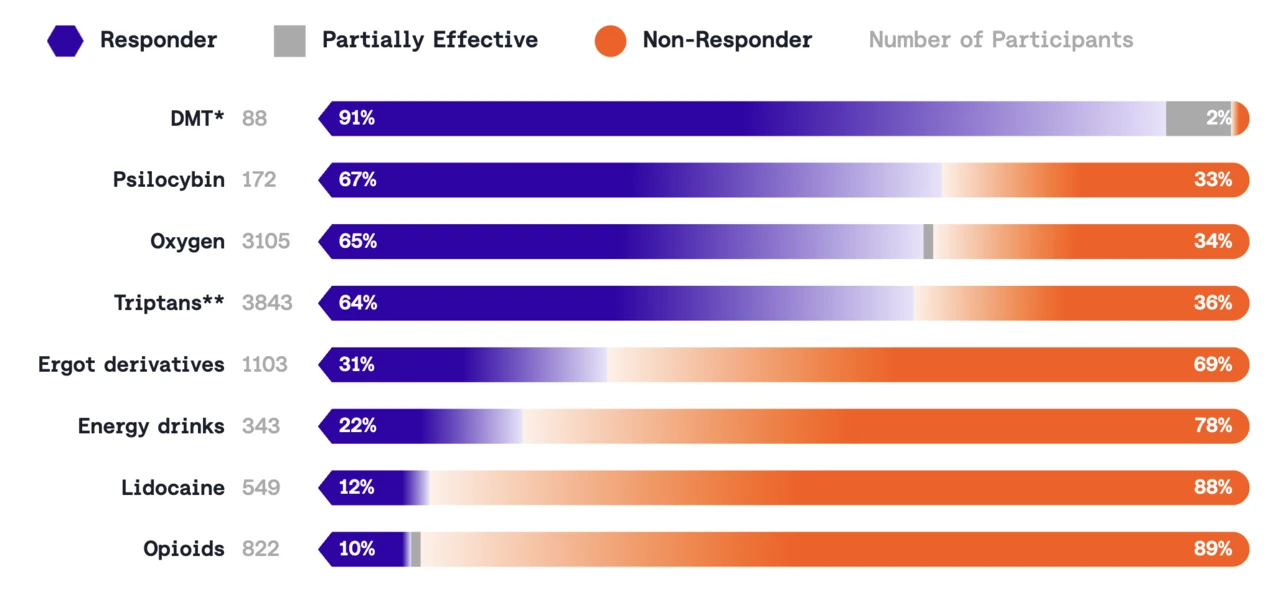
If we aggregate the data from all published surveys on abortive treatments for cluster headaches, we get this:
Dr. Zorrilla concluded with two testimonials from the survey:
It’s also worth noting that 85% of respondents reported having some psychedelic effects. In general, a small, sub-hallucinogenic dose is enough to abort attacks, but some particularly stubborn attacks might require multiple pulls, which can induce a hallucinogenic effect. Also, many patients use ready-made vape pens, which contain higher concentrations of DMT because they are made for recreational use. This is to say, we urgently need a non-hallucinogenic analogue of DMT (like BOL-148, a non-hallucinogenic version of LSD that seems to be highly effective at preventing cluster headaches, and whose phase 2 trial has been stuck for years due to lack of funding).
The second session on DMT was a panel discussion with Bob Wold (president of Clusterbusters), Kevin Lenaburg (Chief of Staff of Clusterbusters), and Eric Frey, a patient who had aborted 200 attacks with DMT in his most recent cycle. As he put it, “That would be a lot of suffering without it!.” Bob himself takes a small dose of DMT every night before going to bed, which he believes is the reason he has been cluster-free for the last three years.
Because my team put together a comprehensive guide on how to use DMT to abort attacks, I was given the chance to introduce it. I emphasized the safety chapter, the importance of discussing DMT with their neurologists (if they’re open to it), and the fact that DMT is not a miracle cure (one patient in the audience mentioned that DMT caused his pain to increase). However, the relief is so profound for such a large fraction of patients that not talking about it is not an option either.
Rhonda Pace, a patient married to another patient (they met at a Clusterbusters conference), talked about the role of “care partners,” a term the community prefers over “caregivers,” which implies a one-directional, giver-taker dynamic that doesn’t match the reality of living with someone with cluster headaches. The toll on partners can be enormous, and they also need care. She talked about the daily struggles of living with “the beast.” As she put it, “This is not an ‘ache.’ It’s a demon from hell.” She also emphasized the importance of these patient conferences, which she considers to be a family reunion.
The importance of good support (family, friends, patient groups) became even clearer to me during a conversation I had with Rob, a chronic clusterhead from the Netherlands, over the closing (Halloween-themed) dinner. “Rob,” I said, “I was once asked, if the pain is so bad, how can people endure it day in and day out? You’ve had clusters for over a decade. What would you tell that person?” “Well,” he said, “my wife and kids are absolutely amazing, and while many treatments don’t seem to work for me, my family keeps me going. During a bad attack, I focus on the fact that they, and my friends, and my fellow clusterheads, will be there when the pain ends. And I know the attack will end. It’s the folks who don’t have that support who are the worst off.” Sadly, though, many patients decide not to go on even when those support systems are in place.
Part of me felt very happy that the patients at the conference had this unique opportunity to meet other patients, partners, clinicians, and advocates. Clusterbusters has built something incredibly valuable. Another part of me finds it devastating that millions of other patients around the world don’t get to experience such a bond. My hope with ClusterFree is to reach more patients in countries where care is virtually nonexistent. Bob Wold himself said, “if you think the issues we’ve been talking about in the US are bad—and they are bad—wait to hear what patients who live in Romania have told me. Believe me, you do not want to live with cluster headache in Romania.”
Our project ClusterInfo is one of our attempts to reach such patients. It’s a website with free resources on how to diagnose and treat cluster headaches, currently available in eight languages. Since launching in late May, we’ve already reached over 11,000 unique visitors, and we’re thinking hard about how to make sure that anyone, anywhere searching for information on cluster headaches can quickly find the information they need. We work with patients, clinicians, and other advocates to ensure the content is accurate, comprehensive, and easy to understand. You can find some web analytics here, in case you’re curious.
For our efforts to disseminate information in countries that Clusterbusters hasn’t had the capacity to address, I was honored to receive an award for excellence in education of cluster headache (which would not have been possible without my amazing team and volunteers, and the donors who have bet on us).

There’s so much work to do, though. We’re a team of 1.3 FTE plus a few volunteers, and given how little advocacy and research exists, any marginal effort to support the cause can have an outsized impact. Get in touch if you want to contribute in some way. Or don’t get in touch—just go ahead and do something if you feel called to (including donating to us or to Clusterbusters if you can). I didn’t set out to start a cluster headache nonprofit. For me, it all began when I decided to answer a research question related to cluster headaches, and one thing just led to another. So if you’ve been thinking about taking that first step, however small (and on whatever cause area resonates with you), consider yourself nudged.1



Addendum: the Consensus Conference
The two days before the beginning of the patient conference were devoted to the first of three editions of the Clusterbusters “Consensus Conference.” The goal of this conference was to bring selected clinicians, researchers, advocates, philanthropists, and community builders to define concrete, ambitious goals for the next three years.

To put things into perspective, there is currently only one preventive treatment for cluster headache that has gone through the full FDA approval process (galcanezumab / Emgality). And it is only approved for episodic cluster headache patients. There are no approved preventive treatments for chronic cluster headache.
In 2024, the NIH spent about $500k on cluster headache research:
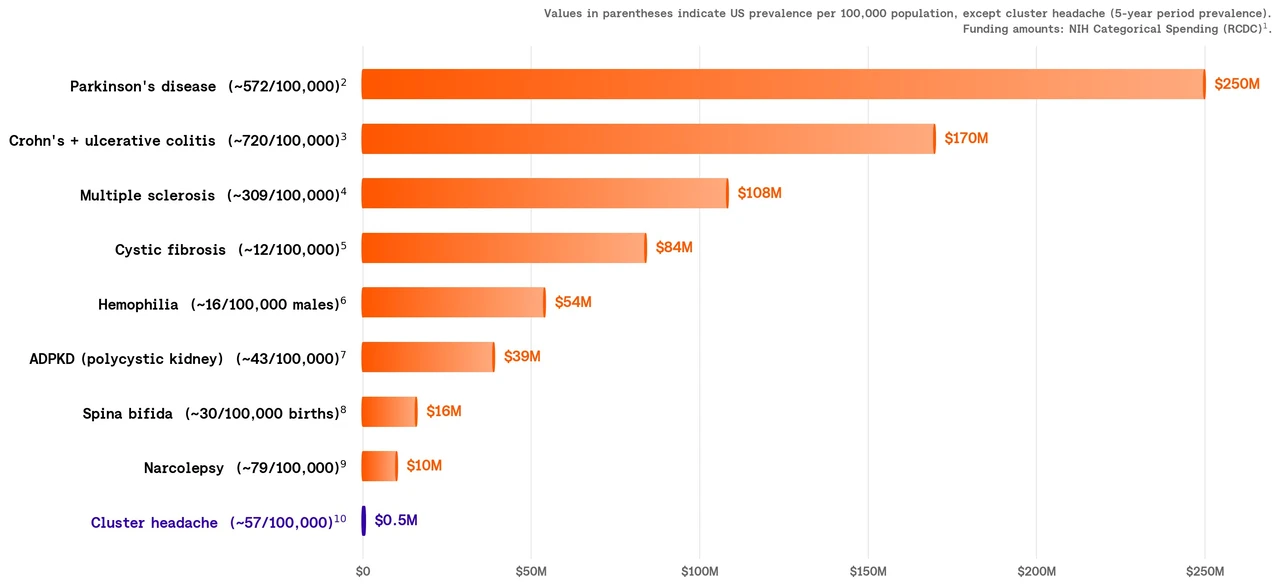
This is not necessarily a failure of the NIH, though. Dr. Michael Oshinsky (Director of the NINDS Office of Preclinical Pain Research, which is part of the NIH) explained that the main reason so few grants have been made to cluster headache research is that almost no one is submitting grant applications. So if you want to get funding for a cluster headache project in the US (or outside it, if you find a US partner), chances are good (and I can point you in the right direction).
While the patient conference was deeply meaningful and rewarding for me, the Consensus Conference, which was more about ideating and strategizing, was very productive. I came away with dozens of new ideas for things to do, from small improvements to our guides to ambitious initiatives that I lack the resources to implement anytime soon. Here are a few:
- Launch a replication contest with a cash prize for the most accurate visualization of what a cluster headache feels like (see, e.g., this jhana replication contest). There could also be an artistic track, but the main focus should be on depicting the pain as accurately as possible.
- Host a program analogous to plsdontkillus for cluster headaches. The memetic potential is huge. (Or, generally, try to create viral social media content.)
- Start more online patient support groups in different countries and languages, like the ones run by Clusterbusters.
- Do some leafleting about cluster headache. Document the whole process.
- Try to gather prevalence data from regions with no data (which is most regions).
- Host patient conferences in other countries.
- Write a cheat sheet for hospital emergency rooms on how to deal with cluster headache patients, and distribute it in local hospitals.
- Look into whether impact litigation against insurance companies that deny coverage for, e.g., oxygen could be effective.
- Create and moderate subreddits for cluster headache in other languages.
- Create a resource pack, or even just a cheat sheet: “I have a cluster headache diagnosis. What now?” Learn from other conditions (e.g., breast cancer).
- Create a public ranking of countries, ranked by how well they treat their patients (probably no country would get an “A” or even a “B” as a grade).
- Try to replicate the HEADACHE Act in other countries.
We plan to gather every year in person and every few months virtually to check in on progress. The excitement and momentum were palpable. I, for one, feel more motivated than ever to get back to work.
Footnotes
-
I’ll soon publish a list of ideas for people specifically interested in reducing extreme suffering in humans. ↩